Time is running out! The Government is consulting on new regulations for natural health products, and submissions close tomorrow, Monday 2 November, at midnight. This is your opportunity to speak up and help protect consumer choice and access to natural health products in New Zealand. We’ve made it easy with a guide to help you have your say in around 10 minutes.Don’t miss this opportunity – make your voice count!
How to use this template:
Copy the text below, fill in the bracketed sections with your own details, and email it to [email protected] before 11:59 pm, Monday 2 November 2026.
You can also send through the online questionnaire at the Ministry of Health consultation page. Personalising it with your own experience will make it more effective.
Subject: Statement on Natural Health Products Regulatory System — Health Consumer
I am writing as a New Zealand health consumer to share my views on the proposed regulatory system for natural health products (NHPs).
I support access to safe natural health products and I want regulation to be proportionate, not restrictive.
I use natural health products as part of managing my own wellbeing. [Optional: add one sentence about what you use and why — e.g. “I take vitamin D in winter” or “I use magnesium for sleep” or “I prefer to try natural options before prescription medicines” or ” I no longer trust my doctor with my health” ( if this is true).
My key concerns with the proposals are:
1. Consumer choice should be a guiding principle. The Government’s own discussion document says regulation should be “proportionate to the risks” and support “timely access”. NHPs are generally lower risk than medicines . Regulation should reflect that difference and not impose medicine-style requirements on low-risk products.
2. I do not want unnecessary barriers to access. New Zealand already has consumer protection laws, food safety rules, and advertising standards. Before adding new layers of regulation, the Government should clearly identify what specific safety gap it is trying to fix. I am concerned that additional compliance costs will be passed on to consumers like me, reducing affordability and choice.
3. I support practitioner exemptions. I believe doctors and other qualified health practitioners should be able to recommend and supply natural health products to their patients, including products from third-party manufacturers. This supports informed, personalised care.
4. I support a transparent ingredient list approach. If a list of recognised ingredients is used to define NHPs, the process for adding ingredients should be transparent and should not exclude ingredients with established histories of safe use.
5. Access matters for people who cannot easily access conventional care. Some New Zealanders rely on natural health products because they cannot get timely appointments, face long waits, or have not found conventional options helpful. Regulation should not make that situation harder.
My recommendations:
Recognise informed consumer choice as a core objective of the new system.
Demonstrate a clear, specific safety problem before imposing new requirements on low-risk products.
Keep compliance costs low so products remain affordable.
Allow qualified practitioners to recommend and supply NHPs within their competence.
Ensure any new rules are transparent, evidence-based, and reviewed over time.
Thank you for considering my submission.
Yours sincerely,
[Your name] [Your town/city]
Notes for Supporters:
You do not need to answer every question in the online questionnaire. You can email a short submission like this one instead
The Ministry has said it may use Microsoft CoPilot to summarise submissions, so clear, simple points work better than long essays
Submissions close Monday2 November 2026at 11.50pm
If you want to make your submission more personal, add one or two sentences about your own experience with natural health products — that carries more weight than general statements
NZDSOS Statement on the Future Regulation of Natural Health Products:
It is a source of relief to those of us working with the vaccine injured, and advocating for the preservation of medical ethics against the corporate takeover of health systems, to see well-organised pushbacks elsewhere. Canada, home of the Freedom Truckers who inspired our own Freedom Convoy and parliament occupation in 2022, has acknowledged the suffering of the covid vaccine injured and bereaved in an official parliamentary hearing, The Allison Inquiry.
Dean Allison is the federal Member of Parliament representing the Niagara West electorate of Ontario in the Canadian House of Commons. Based in Grimsby, on the south-western shore of Lake Ontario, Allison has a background in private business and community service. Elected to the House of Commons in June 2004, he has retained his seat for the past 22 years.
Over half of the entire population of Canada is reported to have received at least one dose of a Covid-19 vaccine. Health Canada’s Covid-19 safety reports document over 59,000 adverse events including 11,000 classified as serious.
It would seem Canada’s under-reporting is much worse even than ours. Doctors and patients have reported extreme difficulty in filing reports, and a consistent pattern by authorities allegedly tasked to investigate reports, of refusing to examine the possibility of safety signals. Combined with a general lack of public awareness to the connection between health problems and the injectable products, this means that the real numbers are likely to be higher by an order of magnitude.
Until last month the only inquiry into the experiences of Canadian citizens relating to the covid response had been the National Citizens Inquiry, launched in 2023 and driven entirely by citizen funding and leadership. Overseen by legal counsel Shawn Buckley, the NCI is now expanding into other related issues.
Allison describes hearing frequently from constituents about the impact of the covid response upon their lives. Sick, injured and disabled people report serious gaslighting from health professionals tasked with diagnosing and treating them, and broad censorship of any attempts to speak about their experiences. These stories impelled him to launch the non-partisan Allison Inquiry in collaboration with Shawn Buckley to “create a neutral forum for Canadians to share their personal experiences of injuries to themselves, or to others, from the Covid-19 vaccine(s).“
The inquiry was held from 8 September until 11 September 2026 at the Wellington Building on Parliament Hill in Ottawa. Over 1,400 witness applications were received from vaccine injured Canadians, with more continuing to come forward. Their experiences will be documented in the final report, and each applicant’s name was read out during breaks in proceedings, in order to be included in the official record.
Forty five injured or bereaved citizens were selected to appear in person at the live event, to describe their experiences and the impact their injury and/or loss has had on their lives. Eighteen expert witnesses with backgrounds in medicine, law, journalism, science and data analysis also provided evidence. Video of each full day, and separate footage of each individual testimony, with a short written summary of each, can be found at this link.
In his opening statement on 8 September 2026, Shawn Buckley revealed the fears expressed by many witnesses, some of whom withdrew testimony due to the stigma they face in a fractured society. “One person was told by a family member, “If I testify, I will never see my grandchildren again.” Another injured witness, who had already lost her mother and a sibling, feared losing the last family member she had left if she testified“. Others were unable to attend due to medical treatment commitments.
Open invitations were sent to all Members of Parliament and Senators, and all media outlets. On Day 2 it was reported that of the 20 seats reserved for the approximately 340 sitting MPs, only two were used. Allison reported that when the Inquiry was first planned, he could not herald any support from his parliamentary peers, but that ultimately about ten MPs attended some of the sessions. Unfortunately all represented the Conservative party, showing the political divide that remains on what should be, and is, a non-partisan issue.
Nevertheless, Allison has described this as a move in the right direction. He says that now MPs are contacting him asking for support to convene local town halls to hear from their constituents. As public perception of what has happened evolves, the conviction of political representatives on all sides of politics is destined to follow. New Zealand seems to be seeing some evolution in the actions of some smaller parties outside parliament and at least one Member of Parliament, current Foreign Minister, Winston Peters.
Similarly, whilst multiple independent media outlets (eg Press for Truth, Rebel News, The Highwire and Wiretap Media) attended and / or reported on the inquiry, legacy media remained absent. Headquarters of Canada’s national broadcaster, the Canadian Broadcasting Corporation (CBC) are a few steps away from the Wellington Building, yet not a single CBC journalist attended.
The absence of the CBC appears to have been eloquently explained by former CBC journalist Rodney Palmer in his presentation to the Allison Inquiry on the difference between “public broadcasters” and “state broadcasters”. New Zealand experienced a similar journalistic fate thanks to the $55m Public Journalism Fund which helped to uphold our “single source of truth“.
The focus of the Allison Inquiry was to give a voice to the vaccine injured, who have been marginalised, ignored, gaslit and smeared as “anti vaxxers” despite taking the products. This is a global phenomenon resulting from a calculated propaganda and censorship campaign.
The Canadian experience reflects that which is taking place globally including here in New Zealand. Whilst the NZ establishment claims to have addressed our covid response through the Royal Commission of Inquiry, human rights breaches and the associated physical harms continue to be ignored and downplayed.
Why do you think, in every single medical euthanasia historical event, who do you think is at the centre of it? It’s the medical system. Each and every time.
This highlights the need for history to be taught in all health disciplines, so that practitioners develop an understanding of the potential harm they are capable of when following rules, protocols and guidelines without appropriate attention to the totality of evidence and ethical frameworks.
One of the most-cited scientists in history, world-leading epidemiologist Professor John Ioannidis from Stanford University is speaking out about the crisis of biomedicine. He rightly states that medical research is being destroyed by vested interests, basic research mistakes and a “deluge of fraudulent research“.
Nowhere has the human cost of this crisis been so obvious, than at the Allison Inquiry. New Zealanders face a very similar cost in health and financial burden. In lockstep with governments worldwide, this fact is denied and ignored by the political establishment and hidden (by censorship) from the public. The injured are abandoned because those in positions of authority, from bureaucrats and politicians to health professionals, refuse to take responsibility for the harms resulting from their actions.
We highly recommend listening to as many of these heartrending testimonies and expert insights as you can, in order to develop an impression of the impact that such injuries have on a person’s life. As well as physical injuries, many describe impoverishment, unemployment, gaslighting, censorship, loss of relationships and more. Through the event a number of MPs admitted during questioning, their own vaccine injuries and bereavements, and there were many tearful moments during the four days.
Carrie Sakomoto – permanent neurological damage following dose 2.
Catherine Christensen – lawyer representing injured active members of the Canadian Armed Forces who cannot testify due to legal constraints.
Michael McNair – army telecommunications specialist with multiple blood clots suggesting spikeopathy, after dose 2.
Kevin Street – permanent neurological damage following dose 1.
Prof Patrick Provost – mRNA and nanoparticle technology expert. Multiple severe symptoms including colon cancer, suggesting spikeopathy, following dose 1. University employment suspended for speaking out.
Prof Denis Rancourt – physicist and interdisciplinary scientist. Analysis of official data showing harms resulted from the response to the announcement of a pandemic, rather than the virus itself. Correlation Canada.
John Grant – insulin dependent diabetes, multiple blood disorders suggesting spikeopathy, leading to permanent lung damage following dose 2.
Nathalie Barbe – disabled by severe neurological and blood disorders after dose 3.
Michael Oesch – severe neurological damage following dose 4.
Jasmeet Grewal – severe neurological and gastrointestinal disorders following dose 2.
Kelly Shorkey – severe neurological disorders following dose 3.
Thor Hart – muscle breakdown and permanent disability following dose 2.
Daniel Freiheit – corporate and commercial law specialist describes problems, some apparently by design, with the Vaccine Injury Support Program.
Dr Jessica Rose – presentation on data analysis of vaccine adverse event reports.
James Freeland – bereaved son of a woman who died from cardiac injury following dose 2.
Marylou Lavalle – bereaved wife of a man who died from cerebral thrombosis following dose 1.
Nicole Maurier – bereaved mother of a young woman who died of lung cancer months following dose 2. Her doctors reported it as vaccine injury and their licenses were threatened.
Julie Ivan – permanent neurological damage followind dose 2.
Eva Caven – eye pain and blindness following dose 1.
Jannine Duffy – severe neurological disability following dose 1.
Dr Charles Hoffe – family physician who has spoken out against the harms caused to his patients at great personal cost.
Carole Avoine – severe neurological damage following dose 1.
Dr Crystal Luchkiw – medical doctor and bereaved sister of a man who planned to testify at the Allison Inquiry but died from myocarditis after dose 2 (symptoms after dose 1).
Patricia Leidl – former World Health Organization, USAID and UNPF health professional with multiple undiagnosable symptoms suggesting widespread spikeopathy following dose 2.
Dr James Thorp – maternal-fetal medicine specialist presents on the harms seen in pregnancy and the neonatal period, and evidence of medical literature corruption.
Mark Chapman – disabled by cardiac, neurologic, and multiple systems disorders suggesting spikeopathy following dose 3.
Crystal Denomme – disabled by complex regional pain syndrome after dose 2.
Julie Woods – co-founder of CanRise. Multiple disabling symptoms suggesting spikeopathy following dose 2.
Drue Taylor – testified virtually due to the health risks of travel. Multiple undiagnosable symptoms suggestive of widespread spikeopathy following dose 1, worsened after dose 2.
Nicole Sedore – blood clot and untreatable brain aneurysm following dose 1.
Dr Gary Davidson – chaired the Alberta COVID-19 Pandemic Response data review, and described the corruption within this task force.
Carol Pearce exhibit – Carol Pearce died immediately following covid vaccination and without investigation, Ministry of Health claimed it was not due to the vaccine.
Toni Lannigan – anaphylaxis and undiagnosed neurological damage including vision impairment following dose 1.
Dr Peter McCullough – Pandemic Lessons Learned presentation on evidence of pandemic planning and vaccine harms.
Dianne Spaulding – undiagnosed haematologic and neurologic damage following dose 1.
Lisa Watson – transverse myelitis following dose 1.
Jasmine Comeau – Guillain-Barré syndrome following dose 2.
These stories are heartbreakingly similar to cases NZDSOS and the Health Forum NZ have been involved with and investigated. The wider community of doctors, officials and politicians are still largely silent.
We end with mention of a particularly cruel twist of fate relating to You Tube CEO Susan Wojcicki and the possible lessons learned from her own potential vaccine injury and death. Wojcicki promoted You Tube’s censorship policies in a 2020 interview with the Washington Post, a 2021 interview on Bloomberg, and at the World Economic Forum in 2022. The so-called “misinformation” she so frequently talked about was often proven to be accurate, but contrary to false information spread by authorities. Despite being a fit and healthy non-smoker, in late 2022 she was diagnosed with lung cancer and she died in August 2024 aged 56.
It seems poignant after such tragic consequences, that You Tube are still hosting The Allison Inquiry videos when once the testimonies were labelled “misinformation” and so severely censored. We take heart that despite the untold suffering, truth is finally starting to emerge and the voices of the vaccine injured can be heard.
The following is a measured and somewhat legally restricted description. Dr Shelton’s case has waited a long time but we must be temperate whilst the process is still active. It is unknown when the judgement will be released.
Dr Matt Shelton’s proceedings before the Health Practitioners Disciplinary Tribunal (HPDT) concluded recently in Wellington. He was first contacted by the Medical Council of New Zealand (MCNZ) in August 2021 about his professional conduct after he sent a text message to his patients alerting them to his concerns about the lack of safety data for covid vaccines especially for pregnant women and children. He advised them to make a considered rather than rushed or coerced decision. It got to the newspapers and within days his GP business was taken from him and he was ejected from the College of GPs.
His Annual Practicing Certificate (APC) was suspended after 3 months of unsuccessfully trying to negotiate a suitable “Voluntary Undertaking” about keeping his concerns to himself. He then appealed the suspension in the District Court in March 2022 and it was overturned. Despite this, the MCNZ threatened to re-suspend his APC if he applied for a new one.
Eventually the MCNZ convened a Professional Conduct Committee (PCC) process in late 2022. The PCC was provided with or ‘came across’ further statements from Dr Shelton – all made before his District Court appeal and already heard by the Court – that ran counter to the official government narrative. His speeches and interviews related to repurposed treatments for covid-19, vaccine safety and efficacy, and concerns re magnetism and contents of the vaccine vials, including whether there were undeclared ingredients and/or contamination in them. Following their deliberations the PCC referred him to the HPDT. It has taken several years for this Tribunal to finally sit and hear the charges.
Of note, the Health and Disability Commission (HDC) carried out its own investigation and found that Dr Shelton had improperly used his practice’s text message system to communicate with his patients and had (curiously) violated clause 6 of the HDC code – the right of his patients to receive information a reasonable health consumer would expect!
The hearing commenced on 30 September 2026 and concluded on 14 October 2026. The charges relate to six videos posted online between May 2021 and March 2022, and a Facebook post. The charges have a number of particulars that appear to relate to statements Dr Shelton made that the MCNZ’s PCC has deemed to be ‘inaccurate’, ‘misleading’, or ‘inappropriate’, possibly also ‘unbalanced’. The details of the particular statements are not entirely clear.
Dr Shelton gave his evidence for a day and was cross examined for nearly a further two. At the end, the Chair commended him for having conducted himself so well ‘for so long and in such a measured way’. His own lawyer noted ‘I don’t think I have ever seen a practitioner give evidence for such a long period of time’.
One of us was granted permission to take notes and this is what the following account is taken from. Dr Shelton is bound by court rules preventing him from saying anything that might be seen to influence the tribunal’s search for the truth. His evidence was very powerful, outlining the journey that had got him to the point where he felt a fiduciary obligation to New Zealanders to make the statements he did. It demonstrated his search for answers to reasonable questions that was continually stonewalled and his subsequent deep concern for the population of New Zealand as he witnessed increasing reports of harm. The scope of his evidence covered much of what NZDSOS has been engaged with over subsequent years. When he finished giving his evidence, despite the strict instruction from the Chair to be quiet, observe and not participate, the audience couldn’t help but burst out into muted applause.
The two days of cross examination by the PCC’s lawyers were repetitive and much of it was “Would you agree that (whatever statement) was inaccurate, misleading or inappropriate?” Dr Shelton tried hard to explain the science and evidence that backed up his statements and his concerns.
Witnesses for the Professional Conduct Committee (PCC)
The two witnesses for the PCC were Dr Nikki Turner (NZ GP, vaccinologist and medical director of IMAC) and Dr Janine Paynter (scientist at Auckland University).
Dr Turner presented her evidence and then was cross- examined for just over a day. Her potential conflicts of interests were drawn out – medical advisor to IMAC (charged with promoting immunisation), involved with writing the Immunisation Handbook (interestingly the chapter on covid vaccines was being drafted in late 2020 well before the Pfizer vaccine had approval in NZ), being on multiple national advisory groups and a member of a WHO strategic advisory group. Dr Turner made a number of interesting points which gave us pause.
Dr Paynter was up next and spoke about the scientific method, ‘reputable science’ and the peer review process. A number of comments regarding mis- and disinformation made it into Dr Paynter’s evidence, despite an earlier comment from the tribunal that such pejorative labels were unhelpful. She said that NZDSOS, Voices for Freedom and Counterspin Media were purveyors of misinformation. This was challenged and removed from consideration. Of note, Hannah Spierer of Counterspin was subsequently given permission to take notes.
Witnesses for Dr Matt Shelton
James Allen, law professor and witness for Dr Shelton spoke about Informed Consent and how it is fundamental to medical practice, and also about the Bill of Rights and Human Rights. He described his disillusionment with his own profession during covid with very few lawyers prepared to defend basic rights. He noted he had also become disillusioned with and disappointed by the medical profession which once he held in high regard.
Dr Phillip Altman (Australian pharmacologist with 40 yrs in drug approval) provided measured but powerful evidence that normal processes had not been followed in the development of the Pfizer vaccine and that the data relied on for approval was inadequate. He reiterated much of Dr Shelton’s evidence that it wasn’t a ‘vaccine’ and fitted prior definitions of gene therapy before definitions were changed. He noted that the product tested in the clinical trial manufactured by Process 1 was not the same as the one mass produced for population wide use. He pointed to the presence of potentially carcinogenic Simian Virus 40 (SV40) gene code in the product produced by Process 2.
Dr Altman also expressed deep misgivings about the pharmacovigilance being undertaken noting that it is all very well to collect and collate data about adverse events, but the data also needs to be analysed. His expectation would be that reports to CARM would have further information including medical records from the affected person gathered and causality assessments using recognised frameworks such as Bradford Hill undertaken. He also provided evidence for the known benefits and benign toxicity profile of ivermectin and hydroxychloroquine.
In the second week Prof. Angus Dalgleish gave testimony on Monday. He covered a lot of territory, drawing on his expertise in viral immunology, vaccine development and as a cancer specialist. He described the refusal of medical journals to publish his and others’ important covid papers, being told they were “not in the public interest”.
On Tuesday Dr Pierre Kory gave evidence and was cross examined. A credentialed expert in intensive care until losing his board certification for his advocacy for treating covid early in the infection, he has become an acknowledged expert on ivermectin and the evidence for it. He described the cherry-picking of trials and fraud to discredit repurposed treatments. Echoing Professor Dalgleish he described being told a major review paper he tried to submit was not likely to engage reader interest. Both spoke to the loss of faith in medical journal independence.
Other witnesses who appeared included Dr Monica Clark-Grill, a long-time GP and bioethicist. She had little truck with the new collectivist (greater good) approach to medical ethics and described the fundamental ethical duty of honesty which public health doctors have when addressing the population.
There were three witnesses to their own or others’ magnetism, discovered post vaccine. Closing submissions for each side will be provided to the HPDT, then their public discussion heard around the 12th of December, likely by audio-visual link.
It may then be many months before Dr Shelton hears the outcome of the Tribunal.
Dr Matt Shelton is a courageous and principled doctor who has stood firmly by his commitment to medical ethics, informed consent and the rights of patients, despite the personal and professional consequences.
The following article written by guest writer Mary Hobbs, was first published in the Daily Telegraph NZ on 29 September 2026, ahead of Matt’s appearance before the Health Practitioners Disciplinary Tribunal (HPDT) in Wellington. NZDSOS is republishing it now that the tribunal proceedings have concluded. We chose to wait until the hearing was over before sharing this tribute, and we will be providing further information and updates on the tribunal in due course.
Unarmed truth and unconditional love will have the final word in reality. This is why right, temporarily defeated, is stronger than evil triumphant. – Martin Luther King
On 30 September 2026, Dr Matt Shelton is scheduled to appear before a Tribunal in Wellington. Not for a well-deserved medal of honour, but for alleged misconduct charges that may result in de-registration as a doctor. The tribunal is expected to take just over two weeks.
Dr Matt is the last of a key group of doctors from New Zealand Doctors Speaking Out with Science, (NZDSOS) called before the Health Practitioners Disciplinary Tribunal (HPDT) for daring to tell New Zealanders the truth and caring enough to warn them about the serious dangers of taking an experimental gene-tech therapy injection – erroneously labelled a “Covid vaccine” – that had minimal, if any, testing and was neither safe nor effective.
Governments of almost every country – flanked by a complicit media – had moved in lockstep, on the orders of a few unelected cabals and technocrats to create panic about “Covid-19” and herd everyone into receiving the experimental gene-tech jab. New Zealanders were subjected to a military-grade psychological programme of fear, locked down, coerced, bribed, and then threatened with loss of employment if they did not receive the jab. No risk/benefit analysis was done. No meaningful information was passed on to New Zealanders that would equip them with the knowledge to be able to provide fully informed consent.
The Medical Council of New Zealand (MCNZ) – despite their claims of being independent from government – swiftly followed in line with the Labour government of the time, leaving the rights of patients in tatters. The Chair of the MCNZ at that time, Dr Curtis Walker, claimed there was “no place” for anti-vaccine statements. That was tantamount to trampling all over the NZ Bill of Rights 1990 (NZBORA) and the rights of patients to have the full information of a medical product so they were able to give fully informed consent, or decline it.
The proof of the dangers of this product were placed before government on countless occasions by NZDSOS and through eminent international doctors.
The MCNZ then promptly singled out NZDSOS, our most outstanding individual doctors and medical staff who risked everything, including their livelihoods, reputations, and registrations – to bring New Zealanders the truth. They endured consistent censorship, and cruel, undeserved ridicule.
Why didn’t Dr Matt Shelton fall into line?
Because, he and his colleagues within NZDSOS could not ignore the principles they swore to uphold, which included: The Hippocratic Oath – First Do No Harm; the Nuremberg Code; the right of the doctor to be able to give his professional opinion of a medical product free of the dictates of government or a medical council; the right of the patient to be told of the risks of a medical treatment, so they are able to provide fully informed consent; freedom of medical choice and the New Zealand Bill of Rights Act 1990 (NZBORA).
Relevant clauses of the NZBORA are in Part 2 and include: 8. The Right not to be deprived of life. 9. The Right not to be subjected to torture or cruel treatment, including the right not to be subjected to degrading, or disproportionately severe treatment or punishment. 10. The Right not to be subjected to medical or scientific experimentation.11. The Right to refuse medical treatment. 13. Freedom of thought, conscience, religion, and belief, including the right to adopt and to hold opinions without interference.14. Freedom of expression. Everyone has the right to freedom of expression, including the freedom to speak, receive, and impart information and opinions of any kind in any form. 16. Freedom of peaceful assembly. 17. Freedom of association. 18. Freedom of movement. 19. Freedom from discrimination. 27. The Right to justice.
These crucial Rights were what Matt, and NZDSOS, sought to defend and uphold, not only for their patients, but for all New Zealanders.
Looking back over the past six years, Matt commented “There was only one obvious right thing to do.” Then he and his NZDSOS colleagues did it. They warned as many as possible, providing balanced factual information to the public through their website. They lobbied government, wrote many open letters to those in parliament, questioned the false narratives, have held packed events throughout the country, invited esteemed international doctors as guest speakers, attracted audiences of over 1,000 people at their events, and are tireless in their efforts to keep the public fully informed. They have written and published factual articles to enlighten others of the dangers of the experimental jab in a climate where there is a paucity of truth and lies are gift-wrapped in the guise of ad agency propaganda and further lies – including “safe and effective”. They have prepared and presented a 382-page report for the Royal Commission of Inquiry 2 packed with proof of injury, illness and death. They have also taken the MCNZ to court. See also here and here. Matt and his colleagues are a formidable army.
Dr Matt Shelton and those in NZDSOS genuinely care. They consistently highlight the plight of the vaccine-injured and bereaved and lobby on behalf of them. They have shone a light on the cruel treatment of the vaccinated, many thousands of whom have suffered severe side effects and then had an almost impossible battle to obtain compensation from ACC while some treasonous members of the medical profession jeered at them when admitted to hospital, alleging their very real side effects were all in their head.
In an interview before the last election, when asked if the “vaccine” injured should receive ACC, National MP (now PM) Chris Luxon astoundingly said they shouldn’t, despite the fact that this is one of the key reasons ACC was established. Labour MP, Hipkins was no better, as he callously alleged they were provided for under ACC when it was clear this wasn’t happening in a straight-forward manner.
The bereaved who had lost loved ones as a direct result of the experimental jab, were often falsely told it had no bearing on the death. Many were offered money for their silence.
Meanwhile, Matt, with the doctors and medical staff of NZDSOS, were going above and beyond in their creation of the New Zealand Doctors Holistic Health Collective (NZDHHC) to help those injured, as well as all New Zealanders who had lost trust in the medical system.
Pfizer’s nine-page list of adverse events, released on the orders of a Judge in the U.S. in 2021, confirmed the truth of what Dr Matt Shelton and his NZDSOS colleagues were trying to make known to New Zealanders. These adverse events were known by the government, as well as the fact that “Covid” wasn’t particularly transmissible or dangerous, the jab did not have the usual testing and there were dangerous side effects, including death. They were also aware that it could cause myocarditis in teenagers from 12–17, but the Labour government chose to hide that and then mandated them to get the “two shots for summer” when in full knowledge of this information, continuing with the lie of “safe and effective”. Over 311,000 New Zealand teens and their parents were never given the information on the risks of this jab that were vital for them to know to provide fully informed consent. Aly Cook and Sue Grey of the Freedom Party did enormous work to uncover this and Katie Ashby-Koppens and Alia Bland of RCR media did a further detailed follow-up.
The truth is, as Dr David Martin confirmed, this gene-tech experimental injection is a military grade bioweapon. Dr Martin’s forensic investigation of the patents connected with that product have proven he is correct. This bioweapon, dressed in the guise of a so-called vaccine, was what was unleashed on the world.
Governments of almost every country, flanked by a complicit media, moved in lockstep on the orders of a few unelected cartels – made up of technocrats and trillionaires – who seek totalitarian world control. The proof has been placed before government on countless occasions and yet they continue to blindly march to the mantra of the colossal propaganda surrounding this jab that can maim and kill. More information on the money trail and the cabals connected with this bioweapon is here and here and here.
Despite the damning, irrefutable evidence that has stacked up over the past five or six years that proves the caution Dr Matt and his colleagues called for was entirely valid, these courageous souls continue to be brought before tribunals by the Medical Council of New Zealand in an attempt to silence and punish them, sending a message to all other doctors. Several have been fined tens of thousands of dollars and were de-registered. If they aren’t de-registered they usually lose their practising certificates temporarily and are put through “re-education programmes”. The Nurses Council (NCNZ) also moved in lockstep. Nurses who spoke out were also fined and de-registered. Both the MCNZ and the NCNZ conducted little more than witch-hunts. More details here. Is there balance in the selection of tribunal members at these events?
The ultimate measure of a man is not where he stands in moments of comfort and convenience, but where he stands at times of challenge and controversy. – Martin Luther King
The irony is that the MCNZ and the government don’t appear to realise that their continued attacks on these ethical doctors and medical staff work against them, for they make the injustice of such attacks so patently clear and this reflects badly on the MCNZ, the Ministry of Health (MOH) and the government. It also makes Dr Matt Shelton and his colleagues even more popular, which culminates in ever-increasing numbers of New Zealanders looking towards NZDSOS for information they can trust. In this way, they give the voice of Dr Matt and NZDSOS expanded reach.
Nor can deregistration make Matt’s many years of service as a doctor disappear, or any spurious reasons be given for deregistration. That won’t wear well for the MCNZ, the HPDT, or government either, especially when considering the avalanche of damning information on the gene-tech jab that is now common knowledge all over the world.
In 2025 Senator Robert Kennedy Jr announced a halt on mRNA funding for 22 vaccine development contracts as the risks outweighed any benefits. His statement was based on the science which seems to have completely eluded the NZ government who continue to march to the drum of a long-outdated script with ever-more resultant injury and death left in its wake.
In light of the overwhelming evidence of the lethality of the bioweapon, it beggars belief that the government still allow it to be administered and the MCNZ continue to bring doctors before tribunals when they have been proven to be right to have advised caution and warn about the potential risks.
One of the key mottos of the MCNZ is to “protect patients and the public”. Punishing doctors for ensuring their patients and the public are aware of the risks so they can give fully informed consent, or refuse to have the medical treatment, is a far cry from “protecting patients and the public”. Dr Matt Shelton and his colleagues at NZDSOS have sent numerous letters to alert them of the dangers. Their letters have mostly been met with a deafening silence.
More on Matt
Matt qualified in the UK as a doctor in 1985 and became a GP. He then worked in NZ on an Overseas Experience (OE) initiative in 1989, and fell in love with the country. He spent some time in anaesthetics and emigrated to NZ to finish his training in 1994, but international medical politics intervened and forced him to return to general practice or return to England to complete his training in anaesthetics. He chose New Zealand. Eventually he taught nutritional and environmental medicine at a post-graduate level for a decade. He had become aware of the limitations of the pharmaceutical paradigm and was interested in seeking the causes of illness, moving to an integrative model as the new millennium turned.
Matt’s family medicine clinic brought him more satisfaction and effectiveness in the way he practiced medicine, as he was working to uncover the foundational cause of disease so the right steps could be taken to restore patients to health. He was heartened by the positive progress that his patients experienced. It also enabled him to work with his patients to seek out where their health challenges were and how to remedy them, whether through diet, exercise, mind-body work, nutraceuticals, and other options. It addressed all aspects of the patient that included mind, body and spirit. It makes sense. (No point in consulting only the body when the mind and spirit are in the driver’s seat.)
Through this work, he was in contact with other medical professionals in the natural/integrative health field. Even then, pre-covid, they collectively sensed that authorities were encroaching on the area of natural health and making moves to restrict it, so they had formed a society immediately before the dark cloud of “Covid-19” loomed on the horizon. At Easter 2021 some of them moved to form NZDSOS to support Sue Grey’s challenge against the mass rollout to the whole country based on law that specified such a product was for limited release, and only to a small number of people. Of course she won and so the government changed the law overnight.
Matt was initially alarmed by the messaging that surrounded “Covid-19” and that the “only solution” presented was a new, previously untried, gene-tech jab. He was concerned for his patients as there was no risk/benefit analysis on it, so New Zealanders would be unable to provide informed consent unless they were told of the lack of safety data. In his professional view, a new type of vaccine would take years to go through sufficient testing, yet this gene-tech “vaccine” was available within months, so that was another red flag.
The government messaging created an environment of fear, along with economic distress and devastation endured through unnecessary lockdowns. Some companies, already wealthy, were given millions to keep afloat while small businesses went into liquidation. There were suicides and over consumption of alcohol and drugs that fuelled domestic violence. Fear was drummed up with the daily rhetoric from the “podium of truth” aided by the collaborative mainstream media. Nothing was mentioned about the potential risks of this new gene-tech at any stage, either pre-rollout, or during the roll-out.
This became too much for Matt. Seeing injuries mount in his own patients, on the day the government suddenly announced teenagers were “eligible” he texted his patients a moderate message recommending caution and that they do their own due diligence. He suggested the NZDSOS website to provide balance to the government’s messaging. The website highlighted the vital, factual information that the gene-tech injection was being released at warp speed with no liability for the pharmaceutical corporations, no list of contents of the vials, no standard safety testing and the usual safety measures were abandoned.
Further Background
The injection was released under “Emergency Use Authorisation” (EUA) because the viable alternatives that were effective, such as ivermectin and hydroxychloroquine (HCQ), were intentionally dismissed and invalidated. Doctors were not permitted to prescribe them. (There is no EUA if alternative treatments are available.) Even worse, the gene-tech jab was a “one-size-fits-all”, enforced on everyone regardless of their medical history, risk factors, allergies, or medical condition.
Please note: There were different batches. Some more dangerous than others. There are also protocols for helping to alleviate harmful effects, so if you have had one of these injections it is important to know that there are things that can be done to help you back to health. Cardiologist, Dr McCullough in the US, has published his protocol here. It is also possible to make enquiries at the New Zealand Doctors Holistic Health Collective, NZDHHC.
Many New Zealanders first heard Dr Matt on the radio with Peter Williams, or saw him in a video clip in 2021 when he was speaking at an anti-mandate event in Wellington, trying to warn of ethical breaches due to the unknowns of the experimental gene-tech jab. Those who know Matt are well aware that public speaking isn’t something he would naturally lean towards – far from it. He would be more likely to want to take off in the opposite direction. But not on this, for he knew that an unforgiveable line had been crossed by the authorities, so he felt there was no alternative but to stand up and speak out. Regardless of his natural reticence for public speaking, when Matt speaks he commands the space and the audience listens, because he communicates with such genuine concern, he has done his research, and he tells the truth. Truth cuts through lies. It resonates. It makes sense and is easy to understand. There is no subterfuge or trickery.
A few months later Matt was at Camp Freedom, speaking publicly again, where many of us who had stood up and spoken out were gathered in February of 2022. Since then, he has been interviewed often nationally and internationally and spoken at many major events.
In an interview with Dr Emanuel Garcia in 2022, Matt said it would have been unconscionable for him to remain silent when he could see the grave danger of the speed in which this experimental gene-tech jab had been rolled out. He insisted on his right to provide his honest professional opinion to his patients and alert them of the risks, for this was the bedrock ethics of what it meant to be a doctor. If doctors didn’t have the foundations of that, the Hippocratic Oath, the Nuremberg Code and the NZBORA, then what did they have? Nothing – little more than the eternal shame of knowing they would be surrounded by the wrecked foundations of a once (long ago) proud profession. Matt wasn’t prepared to accept that, so he had no choice but to speak out.
Matt mentioned in the interview with Dr Garcia that some of his colleagues agreed with his stance but “didn’t want to question or risk trouble”. Brave souls like Matt and his colleagues often find plenty of room at the front, while others fade into the background, heads down, eyes shielded. Those who questioned were spurned, with practicing certificates suspended, including Matt’s.
Matt appealed in court. The Judge took his side, telling the MCNZ to reinstate Matt and get him back to work. Matt did get his licence to practice back, albeit very briefly as the MCNZ immediately created new charges and started suspension proceedings within a week of the Judge’s decision. It seemed, to many, that was a substantial overreach by the MCNZ, tantamount, surely, to contempt of court?
Few men are willing to brave the disapproval of their fellows, the censure of their colleagues, the wrath of their society. Moral courage is a rarer commodity than bravery in battle or great intelligence. Yet it is the one essential, vital quality for those who seek to change the world which yields most painfully to change – Robert Kennedy
There were further murmurs of quiet approval from previous colleagues on the quiet, but when push came to shove they melded into the shadows. Instead of standing together, most doctors feared to speak out. They kept their heads down, remained silent, followed orders, and fell in line. Some, perhaps, initially believed the military-style propaganda assault; some didn’t, but went along with whatever it took to keep their job. Others, apparently, did kick up a quiet behind-the-scenes fuss, for over 11,000 health-workers were given exemptions from having the jab themselves while their patients and other New Zealanders were forced to do so, or lost their jobs and were shut off from society, ostracised for refusing to submit to it.
If most doctors had simply stood by their families, their patients and NZDSOS, and hadn’t remained acquiescent and silent as the medical rights of all New Zealanders were trampled over, then the current devastation in our country would have never gained a foothold. But, they made their decision and were hollowed out from within, untethered now from medical ethics, honour and conscience with no visible upholding of the Hippocratic Oath, The Nuremberg Code, or the NZ Bill of Rights Act.
It is not too late for the doctors who remained silent to speak out. Until the day they do, and until they stop taking the money and rewards for the majority of their patients being jabbed, they will not stand as any medical practitioner of ethics, soul and substance – just a parody of what was – an empty vassal for the pharmaceutical industry, and the military-industrial complex, in tandem with government and the various medical councils, to manipulate and order about as they please. Even now, they can still unleash themselves from that unenviable hell. It is very late to do so, but it is possible, if they speak out, blow the whistle on what they have seen of the carnage, and reach out to other like-minded individuals such as those in NZDSOS.
The longer the military-grade psychological “Covid” operation continued, the louder the alarm bells went off as the Prime Minister and MPs – with no medical experience – all weighed in on giving medical advice to “get the jab”. The infamous comment that “We are your single source of truth” really took the cake.
Pregnant women and those planning to become pregnant, as well as children, would be some of the most vulnerable to side effects. It had been an unwritten law in medicine that pregnant women shouldn’t have any pharmaceutical drugs during pregnancy, unless imperative. This had been a rule since the dark days of thalidomide when a pill given to pregnant women to alleviate morning sickness resulted in babies being born with missing limbs and other deformities. As a result, all drugs were avoided in pregnancy, as well as alcohol and smoking. Even Pfizer in the US had suggested pregnant women avoid their so-called “vaccine” but the Ardern-led NZ government gave no such warning. Matt did. NZDSOS did, as well as other like-minded Kiwis in the Freedom movement.
In terms of history, it hadn’t been that long since 1945 and the horrific medical experiments conducted in the concentration camps by the mad Mengeles and others that led to the Nuremberg Code. This document made it very clear that no one was to be experimented on medically unless they were fully informed of the risks and dangers of such experiments and gave their willing consent. Vera Sharav, survivor of Auschwitz, quotes the Nuremberg Code here. The Declaration of Helsinki 1964 further endorsed the principles of The Nuremberg Code 1947.
As mentioned, the MCNZ states its prime purpose is to protect the public and patients. It also states it is independent from government. It is difficult to see how they were protecting the public, patients, or acting as though they were independent from government if they weren’t advising of the risks of this gene-tech. If the MCNZ had insisted that the ethical principles of fully informed consent, the Hippocratic Oath (First, Do no Harm), the New Zealand Bill of Rights Act 1990 (NZBORA 1990), and the Nuremberg Code must be honoured and held sacrosanct, before anyone received one of these shots, then that would have protected the public and patients and it would clearly show them to be independent of government. But the MCNZ, and other medical councils around the world, appear caught in the grip of a private international Rockefeller-linked organisation that has been in existence since 1912. Dr Bruce Dooley blew the lid off that here and here.
Instead, as mentioned, the MCNZ appeared to bypass the key foundations and dictated to doctors that they were all expected to be injected with the novel gene tech therapy and there was no place for any anti-vaccine statements. Why would they act in this manner? This NZDSOS article provides some possible answers.
From a lay person’s view — and as a former NZRN many years ago – it wasn’t the job of the MCNZ to dictate to doctors that they weren’t permitted to express their professional opinion of a new, virtually untested, gene-tech jab with a high rate of side effects that crossed the line. Yet, I repeat, they did, virtually bypassing the ethical obligations of each doctor and ordering them to violate the patient’s right to be able to provide fully informed consent, as well as violating the NZBORA, the Nuremberg Code and the Hippocratic Oath. Then the usual methods used by MCNZ to muzzle doctors ensued including; losing the right to practice, being brought before a tribunal, fined extortionate amounts of money and, in some cases, de-registration. A modern-day Inquisition. A hallmark of fascism or communism.
For astute New Zealanders, the actions of the MCNZ created an immense distrust of those who remained within the fold of such an organisation. How could the remaining doctors be trusted if they were forbidden from giving their professional opinion of a new gene-tech jab and forbidden to inform their patients of the contents of the vial and likely side-effects?
That’s what Matt and his colleagues at NZDSOS endeavoured to do – ensure New Zealanders had the information to make balanced decisions.
The previous Ardern-led government appointed Simon Watts onto the MCNZ and he served as Deputy Chair for some years. As NZDSOS made clear in a recent article, Deputy Chair Simon Watt appeared to have a direct conflict of interest as he had negotiated the Pfizer procurement contract for the government, but then sat on the Council “adjudicating complaints against vaccine-critical doctors.” That seems a far cry from “independent from government”.
In June 2026, the MOH MP, Simeon Brown made the decision to decline the reappointment of Simon Watt, the Deputy Chair of the MCNZ, and the Chair, Dr Rachelle Love. The Minister stated “The Medical Council has become increasingly distracted by politics instead of focusing on its core responsibilities of improving patient outcomes and ensuring New Zealanders can get the care they need, when they need it.” This decision appeared to be hot on the heels of a MCNZ announcement about “cultural privilege”. There were howls of protest from sponsored media about the Minister declining to reappoint Dr Love and Simon Watt, but not so much as a whimper on the original government appointment of Simon Watt, the lawyer who played that key role in the government negotiations with Pfizer during the tenure of the previous government.
Despite the world being awash with factual information from international experts publicly stating that the experimental injection is neither safe or effective and doesn’t prevent transmission — and when Pfizer had long-since released the nine-page list of adverse events — the NZ ‘caretaker government’, on 3 November 2023, extended provisional consent for the experimental Pfizer jab for a further two years and then immediately moved to fully register all variations of the jab, and even included the formulas now redundant.
This happened all while Dr Matt, the NZDSOS and many of their colleagues all over the world were exposing the dangers. For example, in addition to Dr David Martin defining this injectable as a bioweapon, Dr Mike Yeadon, who worked for Pfizer for over 20 years, concurred and explains why here. Sasha Latypova, a former pharmaceutical executive, gives her well-researched view that “an intent to harm has been taking place under the guise of a pandemic.” She states here that it was the US military that authorised the jabs and her video explaining that is here.
After carefully viewing the information and watching the serious anomalies in NZ, Dr Matt and the NZDSOS team, concurred with their international colleagues that it was a bioweapon. This was based on what they had witnessed here, with what they described as: “the dysfunction of the organisations, authorities, institutions, laws and people that are supposedly in place in this country to protect us. They list specifics here.
This, in my view, is a war that has rapidly transpired to be a battle for the human soul, the Divine Essence, and the human being we recognise as mind, body, and spirit, capable of love, compassion, caring and humanity. For those who scoff at this statement and label it under yet another conspiracy theory, they may like to review the words of Yuval Harrari, the side-kick of Klaus Schwab the former head of the World Economic Forum (WEF) –– one of the front groups for key unelected cabals and technocrats – when he arrogantly told the world they could forget about having a human soul and freedom of thought as humans was over, as they were now hackable animals. They seek to belittle and degrade the human spirit at every turn, because they are aware of the power of the spirit, within each of us, if most of us stand up and peacefully say, No.
As mentioned, Dr Matt Shelton and his colleagues advocated for medical freedom of choice, the right to fully informed consent where the patient must be told of the side effects of any medical treatment so they are able to give fully informed consent, or have the right to decline it. The government ran roughshod over all of those rights. The real dangers of chronic illness, a shattered immune system, a maimed body, and death were hidden and instead the public was implanted with the despicable lie of “safe and effective” in a psy-op propaganda campaign that could be more accurately described as an implanted propaganda phrase repeated incessantly – and that went into the brain “believed”.
It is not easy to stand up and speak out as Matt and others have done. It takes the courage of a lion. He would downplay his role and be the first to try to dissuade anyone from considering he was brave. The pressure is immense on these courageous souls of NZDSOS, but nothing compared to the soulless black hole of oblivion one would find oneself in if turning one’s back on the most important truths of this lifetime and countless others. Humanity now teeters on the brink of oblivion, as mad scientists manipulate genetics through military bioweapons.
Parliament is neck-deep in the evidence of the lethality of this bio-weapon and others coming down the line that are intended. They are fully aware of chronic illness, the injury and deaths from it. All off the scale.
They are still being given.
If you are inspired and grateful for the enormous work Dr Matt Shelton and his colleagues at NZDSOS have done on behalf of us all, or if you have been able to click on the plethora of material at NZDSOS to help communicate the truth, that’s terrific, but please do hit the DONATE button and contribute to this mighty group. Be generous, do what you can afford. Contact friends who would also like to do the same. That offers tangible help to get the message out further, the gene-tech jab discontinued, and to bring those pushing this agenda to account. If you would like to do additional things to help, please click the TAKE ACTION button. Please get involved. Every step Dr Matt and these souls within NZDOS take is done for all of us. It is time we all contributed so we can have the New Zealand we want. Your help makes an immense difference. It lightens the load. It shines light, too. Thank you.
These fearless souls are steadfast, resolute, determined. Shoulder-to-shoulder they stand and continue to stand, maintaining the ethics we all thought a doctor would stand by as part of their profession. And Dr Matt Shelton is one of these fine doctors at the forefront. They have endured a parody of justice and false accusations. They have been knocked down and yet they still get back up, but stronger. More determined. Invincible.
As the lights went out in New Zealand and darkness enveloped our country, these courageous souls continued to speak out regardless of the cost. They shone their light on the lies with the truth. They are shining lights in a world of darkness.
Dr Matt Shelton would say that he has been blessed to be one of many of the key colleagues at NZDSOS and also the first to deny that he is a leading light for all at the NZDSOS as well as many thousands of New Zealanders and people all over the world. He would consider he was just doing what needed to be done. There was no other option for him and he has never once faltered. He is determined and resolute in bringing out the truth. He always will be.
It would be great to see support for Dr Matt Shelton as he fronts up to this tribunal in Wellington from Wednesday, 30 September 2026 to Friday, 16 October 2026. It is at the West Plaza Hotel, 110 Wakefield Street. It commences at 9am. Respectful and dignified behaviour by attendees would help Matt the most.
Matt, and NZDSOS: Thank you for your service, your dedication to medical ethics, putting yourself in front of your patients to defend them, and all New Zealanders. Thank you for standing in defence of medical ethics and the rights of every New Zealander.
Thank you for going above and beyond what anyone should be called to do to keep the honour and integrity of your profession intact. Thank you for your perseverance, integrity and dedication to the truth, regardless of personal consequences. Thank you for putting in the countless hours, day and night spent on validating evidence, writing, reporting and making known the truth, and working so hard to turn the trajectory of our country towards the light.
In the darkest of New Zealand’s days to date, you and the NZDSOS team shine out, and are indeed key among those who dispel and darkness with your powerful light of truth.
It is from the numberless diverse acts of courage and belief that human history is shaped. Each time a man stands up for an ideal or acts to improve the lot of others or strikes out against injustice, he sends forth a tiny ripple of hope, and crossing each other from a million different centres of energy and daring, those ripples build a current that can sweep down the mightiest walls of oppression and resistance. – Robert Kennedy
A Call to Action: Take This Letter to Your Election Candidates
With New Zealand’s general election on Saturday, 7 November 2026 fast approaching, now is the time to ask candidates where they stand on the unanswered questions surrounding the c-19 response.
NZDSOS has written an open letter to MPs and prospective candidates calling for an independent examination of the evidence, proper investigation of people who believe they have been injured and bereaved families, and an end to the dismissal of legitimate questions.
As our letter states: “Political power is a trust, not a shield.” Those seeking public office must be prepared to answer difficult questions, explain their positions and be held accountable for their decisions.
Now is the time for us to put the pressure on and take action. Print off our PDF letter or download it and send a copy electronically to your local MP and election candidates. Ask them to read it, respond to the three requests, and make clear where they stand before you cast your vote.
Don’t let the questions go unanswered. Get the letter into candidates’ hands and make it a starting point for conversation in your community.
The connection between poverty and ill health is well established in poor nations, where poverty increases the risk of illness and injury, which in turn limits the individual’s ability to earn an income whilst simultaneously increasing the need to pay for medical care. Across the globe many millions live with crushing debt caused by medical costs, often relating to preventable conditions, and very often relating to medical error.
Prevalent in the vaccine injury testimonies at Canada’s Allison Inquiry in Ottawa from 8-11 September 2026, was the experience of impoverishment caused by loss of income combined with unaffordable health care costs. As medical doctors working with the vaccine injured, we can confirm a similar trend amongst New Zealand’s vaccine injured.
Crowdfunding for Medical Costs
Defined as the practice of raising money from a large number of people, typically via the internet, crowdfunding has become an essential feature in the lives of those experiencing unaffordable health care costs. Today’s social media is teeming with video footage of young people seeking financial support to afford treatment for life threatening conditions such as cancer and motor neuron disease. All use crowdfunding platforms as a collection point for those wishing to contribute to their cause.
Crowdfunding platforms are private companies providing a central point for donors to send funds. The platform typically takes a percentage of donations before forwarding the rest to the allocated bank account of the recipient. There are at least 75 such platforms in operation.
Two of the best known crowdfunding platforms used in New Zealand are GiveALittle and GoFundMe.
Headquartered in Auckland with eight staff, GiveALittle was founded in 2008 and acquired by Perpetual Guardian in 2020. With assets worth $4 billion, Perpetual Guardian describe themselves as New Zealand’s premier provider of estate planning services.
GiveALittle take a service fee of 5% of all donations, which is reduced to an average 2% cost to recipients due to most donors adding the service fee to the amount of their donation. Since 2008 they have taken a total of $361.2 million in donations, suggesting total company earnings of over $18 million.
Also founded in 2008, GoFundMe was rebranded in 2010 and became the world’s largest crowdfunding platform in 2017. The company takes 2.9% + 0.30c per donation. More than $50 million is raised each week, suggesting total company earnings of more than $1.45 million per week.
Impersonating Crowdfunders
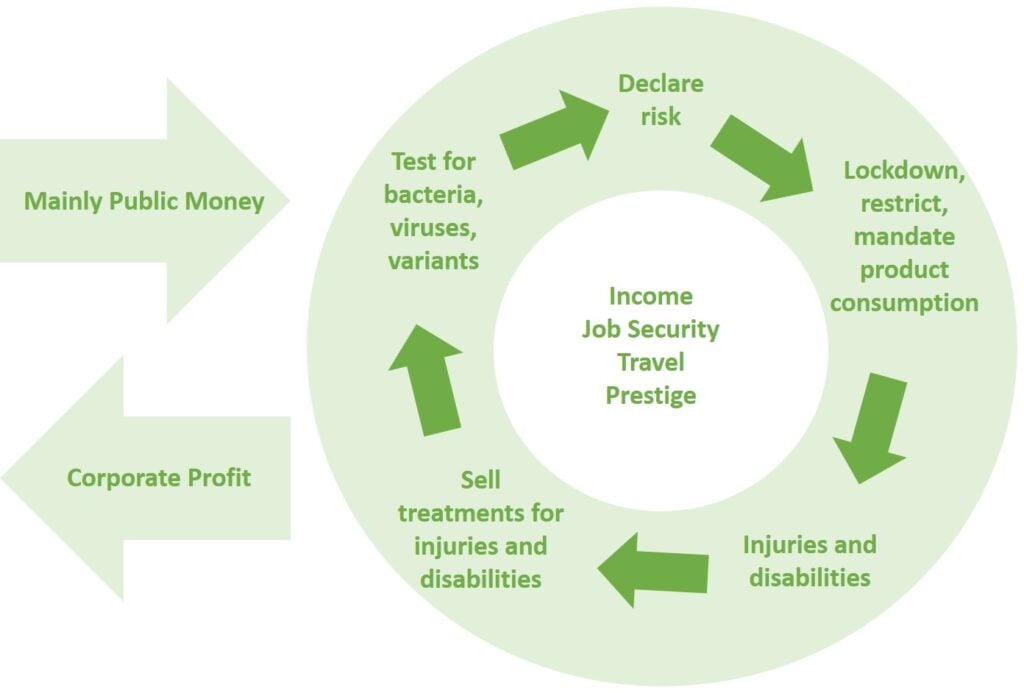
It is no secret that crowdfunding is big business. Whilst serving a useful purpose, these platforms are yet another beneficiary in the pandemic business model that oversees harm and impoverishment for profit.
Image captured for criticism/review and reporting current events under Fair Dealing – The Copyright Act 1994
It should come as no surprise to anyone who understands the corruption of the pandemic industry, that an explosion in crowdfund platform impersonators is being seen on social media. The scam is very simple, and very easy to detect.
Imposters create a webpage that looks similar to any other crowdfunding platform, with a logo, an endearing or official-sounding name, and all of the appropriate buttons (Home, About Us, Contact Us, FAQ and Donate). They add the stolen photographs, video footage and edited profile of genuine fundraisers.
The page appears entirely genuine and often tens of thousands of dollars have been raised by unsuspecting donors. The only button that works on these fraudulent sites is the “DONATE” button. All other buttons lead to nothing.
We suggest that this is an inevitable evolution in a culture that is steeped in fraud and crime. The vaccine injured have been silenced, denied and attacked for over five years now. It is only natural that the next step would be to divert funds from their cause, abusing the empathy of decent people, in order to acquire ill-gotten gains.
Please be careful where you channel any financial contributions during our burgeoning health crisis. Explore any webpage posing as a crowdfunder. Do all of the buttons work? For example is there a Home Page? Is there an About Us page? Are there FAQs to read? Can you find what percentage of your donation will go to the platform vs how much will be sent to the actual cause? Is there a way to contact the website owners? Or is the only working website feature a Donate button likely leading to the private bank account of someone committing fraud?
There are ways to donate directly to the vaccine injured, bypassing all crowdfunding sources by making contact through those who support them such as our own NZDHHC Clinic.
The covid era has exposed a litany of organised crime within the systems that most of us once trusted as being grounded in legitimacy and integrity. None more so than the structures that our health care and research systems are built upon. Here, we take a look at the patents system being used by corporate executives, public officials and the “experts” they finance, to exploit and commoditise humanity (as well as the animal and plant kingdoms).
What is the Patents System?
The patents system ensures legal protection for a limited term to the person or group who created a new invention or discovered new knowledge. A patented invention can only be produced, used or sold, by its inventor(s) for the term of the patent. In exchange for these exclusive rights, the inventor(s) must share the technical information about their invention for the public to learn from.
Naturally occurring phenomena are discovered rather than invented, which excludes them from patent eligibility unless they have been modified. Pathogens which have been genetically engineered to be different than their natural origin are an example of patent-eligible products.
Dr David Martin has been tracking and monitoring violations of international conventions on biologic and chemical weapons research and manufacturing for three decades. In this detailed 2021 interview with James Patrick at Planet Lockdown, Dr Martin explains the corruption of the patents system and the evidence that the patents system provided, of SARS-CoV-2 having been altered in a laboratory.
Dr Martin explains that the patents system hides, in plain sight, a lot of intellectual property theft and misappropriations of technology. This is especially prominent in the area of biological and chemical weapons, toxins and ammunitions. “People are proud of the fact they could get patents on things which probably should never have been the subject of research let alone commercial controls and market manipulations“.
In a detailed analysis of patent filings Dr Martin found that at least 80% of patents issued to large pharmaceutical companies are initially rejected for not conforming to patent law. The rejections are often overridden by back-room deals without the product meeting legal or statutory requirements.
Pandemics and Patents: The Biowarfare Business Plan
Describing the use of pathogens to create a market for products, Dr David Martin exposed the very long history of coronaviruses in a presentation at the European Parliament in June 2023. View the slides here. See his second European Parliament presentation in September 2023, at this link.
Coronavirus as a model of a pathogen was isolated in 1965 … a pathogen that could be used and modified for a whole host of reasons … In 1966 the very first CoV coronavirus model was used as a Transatlantic biological experiment in human manipulation … a data sharing experiment between the United States and the United Kingdom … and in 1967 we did the first human trials on inoculating people with modified coronavirus …
Over the years many patents have been filed relating to pathogens with pandemic potential. For example, a year after the 2002 SARS outbreak which was alleged to have claimed over 700 lives, the US Centers for Disease Control filed an application to the US Patents Office for a Coronavirus isolated from humans. The patent discusses modifications and citations providing evidence that SARS-CoV was used to assist in the creation of chimeric viruses using recombined genetic sequences.
In typically inverted language, WHO claims that the PABSS would “make the world safer from future pandemics“. In fact, the PABSS will clearly increase gain of function research capabilities by making viral genetic sequences available online. The intent of this is to scale up financial commitments by governments who are embedding pandemic preparedness into budgets and policies across multiple sectors.
In 2015 researchers including Ralph Baric, virologist at the University of North Carolina (UNC) Chapel Hill, filed a patent for Methods and compositions for chimeric coronavirus spike proteins with the US Patents Office. The chimera in this patent is named HKU3-Smix.
Chimeric: an entity composed of cells, tissues, or genetic material from two or more genetically distinct sources.
Chimera: a fire-breathing hybrid monster from Greek mythology, composed of a lion’s head, a goat’s body, and a serpent’s tail. Born to the monstrous parents Typhon and Echidna, this creature terrorized the region of Lycia until it was slain by the hero Bellerophon riding the winged horse Pegasus.
The summary of the invention in the patent for HKU3-Smix describes the manipulation of four different regions of the spike protein using coronaviruses HKU3, SARS-CoV and BtCoV279. Independent researcher Jim Haslam suggests that evidence shows HKU3-Smix is in fact SARS-CoV-2 and is calling for an investigation.
The HKU3-Smix patent, granted in February 2018, outlines eliciting “an immune response” in infected subjects to justify implementing testing, preventative and/or treatment interventions. This is gain of function research being used to create a market for medical products.
It is clear that Baric knows exactly what he is involved in. His 33 page curriculum vitae includes 107 professional development / invited presentations, including an event in 2005 titled Synthetic Coronaviruses. Biohacking: Biological Warfare Enabling Technologies.
In the below clip Baric boasted to his audience about the profits that can come from a pandemic. In January 2019 Belgium’s 2009 Swine Flu commissioner Marc Van Ranst, similarly boasted about his experience in manipulating public perception to an audience at Chatham House in London which included UK government pandemic advisors.
Another example of the many thousands of actors in the organised crime syndicate abusing science to implement a protection racket, is Dutch virologist Vincent Munster, Chief of the Virus Ecology Section at the US National Institute of Allergy and Infectious Diseases (NIAID) Biosafety Level 4 Rocky Mountain Laboratories in Montana. Munster and a colleague were detained by border agents in Detroit in January 2026 and charged with attempting to smuggle vials containing Mpox, chickenpox and human DNA from the Democratic Republic of Congo.
Should we take comfort from these arrests that, at some level at least, legal boundaries are being enforced?
Deserving of mention here is biowarfare researcher, British Zoologist and former head of EcoHealth Alliance, Peter Daszak who we have mentioned previously. At a 2016 workshop on Developing Medical Countermeasures (MCMs) for Coronaviruses, Daszak claimed that:
“Until an infectious disease crisis is very real, present, and at an emergency threshold, it is often largely ignored. To sustain the funding base beyond the crisis, he said, we need to increase public understanding of the need for MCMs such as a pan-influenza or pan-coronavirus vaccine.
A key driver is the media, and the economics follow the hype. We need to use that hype to our advantage to get to the real issues. Investors will respond if they see profit at the end of process.“
In a 2019 interview with New York University virologist Vincent Racaniello, Daszak described his work, largely funded by US federal money. As well as promoting the One Health approach being embedded into World Health Organization’s pandemic legislation for the purposes of justifying global governance, he admitted to working on a number of viruses listed by GAVI as being the possible cause of “the next pandemic” including Rift Valley Fever, Nipah and Coronaviruses. In reference to coronaviruses, he admitted to conducting gain of function research in partnership with Ralph Baric.
“… coronaviruses are pretty good, you can manipulate them in the lab pretty easily, the spike proteins drive a lot about what happens … you can get the sequence, you can build the protein … insert it into the backbone of another virus …“
Records released in 2023 to Judicial Watch confirmed that EcoHealth Alliance collaborated with the Wuhan Institute of Virology to create mutant viruses “to better predict the capacity of our CoVs [coronaviruses] to infect people.” In January 2025 EcoHealth Alliance and Daszak were defunded and debarred for five years by the Department of Health and Human Services for their role in the covid pandemic.
By April 2025, Daszak had started a new non-profit, Nature Health Global, whose work includes claims of “preventing future pandemics” and “countering disinformation and protecting science”. Illustrating the collaborations within the biowarfare business model, by June 2025 Nature Health Global had signed a five year contract with Springer-Nature, to manage the high-impact quarterly peer-reviewed journal EcoHealth.
Patents Beyond Viruses: The Cancer Pandemic and Coinciditis
In 2013 Moderna filed a patent for Modified polynucleotides for the production of oncology-related proteins and peptides to the US Patents Office. Inventors of the patent are listed as Moderna CEO Stephane Bancel and colleagues. In February 2022 Frontiers in Virology published an article describing a “highly unusual” exact match between this patent and a 19-nucleotide portion of the furin cleavage site on the SARS-CoV-2 spike protein.
When asked about this incredible coincidence in a February 2022 interview, Bancel dismissed it with a confident chuckle, stating “our scientists are looking into those data to see how accurate they are“. No doubt the same scientists who patented the nucleotide sequence investigated themselves to find no wrongdoing. Read more on this, and on Bancel’s connections with the Wuhan Institute of Virology, at John Leake’s Focal Points article.
Profits Beyond the Pandemic
In order to offer lay-friendly insights to those attempting to make sense of this issue, we have kept this summary brief and as uncomplicated as possible. Thousands of virologists and scientists are conducting similarly fraudulent research under the guise of “public health”.
The covid plandemic has set the scene, and offers a template for ongoing plundering which threatens our very lives, let alone our relatively free existence up until recent times. However, the Epstein class – those committing high level crimes with infinite entitlement and zero accountability – is being exposed via the trails of money and patents, as uncovered by the likes of researchers we share below. It is up to the people, what we do with this information.
Professor Michael Baker’s Flu Vaccine Claims: The Evidence He Isn’t Discussing
Professor Michael Baker has been all over New Zealand media this winter, warning of record high deaths in the worst flu season in a decade and promoting the flu vaccine as protection against heart attacks and strokes. But the research he cites is weaker than his messaging suggests, and the modifiable risk factors he ignores are stronger. And there is theory and evidence to suggest our immune-injured population is uniquely vulnerable.
The Cardiovascular Claim
Baker claims influenza vaccination reduces heart attacks and strokes by about 30%. There is indeed some data from high-risk groups. A 2021 Norwegian study found reduced relative risk of heart attack (RR 0.72), stroke (RR 0.77), and pulmonary embolism (RR 0.73) among cardiovascular medication users. A 2022 Alberta study of 4 million adults found reduced stroke hazard (HR 0.775).
However both studies were observational and neither reported the number needed to vaccinate to prevent one event, nor the absolute risk reduction from which it could be calculated. The relative risk reductions sound impressive, but without knowing the baseline risk, the absolute benefit for any individual remains unstated. This is a recurring feature of the evidence base Baker and his colleagues rely upon.
Trying to be fair, there is a plausible mechanism. Influenza infection (like all infections) triggers inflammation, and clotting tendency goes with it. But this is not the vaccine “protecting the heart” – if it does prevent an infection then it prevents a trigger. And the benefit concentrates in those already at high cardiovascular risk, whereas vaccines go predominantly into healthy people who have a different risk-benefit calculation.
If Baker is going to claim flu jabs are good for cardiovascular disease, then what about the covid-19 injections? Those same risk factors of clotting, endothelial dysfunction and myocardial inflammation are precisely the ones the gene transfer products can cause. The difference is that Baker looks in one direction only. If influenza vaccination reduces cardiovascular events by preventing an inflammatory trigger, what does repeated mRNA vaccination do to that same system when the spike protein it produces is itself pro-inflammatory and pro-thrombotic? The question answers itself. You cannot claim credit for preventing a trigger while ignoring the trigger you inject.
What Baker Does Not Mention
Vitamin D. A meta-analysis of 25 randomised trials found a 12% reduction in acute respiratory infections overall, and a 30% reduction in those with levels below 10 ng/mL. A 2026 Harvard analysis of over 36,000 adults found those with the lowest levels were 33% more likely to be hospitalised.
Zinc. A 2026 review in Nutrients found zinc supplementation reduces the incidence and burden of respiratory infections, particularly in children with recurrent disease and in zinc-deficient populations. Starship Hospital has been overwhelmed this winter. Zinc deficiency is common in growing children.
NAC. A randomised double-blind trial of 262 subjects found long-term NAC (600mg twice daily) significantly reduced the frequency, severity, and bed-rest days of influenza-like episodes. Among those with confirmed infection, only 25% of the NAC group developed symptoms compared with 79% of the placebo group.
Hand hygiene. A 2023 Cochrane review found hand hygiene reduced acute respiratory illness by 14%. School trials in Bangladesh and Egypt found 50 to 53% reductions in laboratory-confirmed influenza.
Saline nasal rinses and gargles. Multiple studies support their role in respiratory infections, including covid-19.
These interventions cost almost nothing and have no serious adverse effects. Baker does not mention any of them. The vaccine is the only solution offered.
Burrell and the Absence of Numbers
Dr Buzz Burrell, Chair of General Practitioners Aotearoa, ‘joined the choir’ on RNZ’s Saturday programme this winter to discuss “surviving winter flu season.” He was non-specific about the degree of protection the vaccine offers. He did not mention the number needed to vaccinate to prevent one case. He did not discuss absolute risk reduction.
So we have two mainstream doctors, both promoting the flu jab, neither quantifying its benefit, neither discussing the evidence for prevention strategies that work.
On Flu Jab Safety, Baker Is on More Solid Ground, if He Ever Mentions It
The flu jab is held up as being safe, reliably enough that other vaccines are compared to it. But here is where some of the most damning evidence against the covid gene transfer products comes from. Baker’s claims of their safety have to deal with proportionate reporting ratios of complications, for instance related to pregnancy and women’s health, of hundreds of times greater than for the flu jab, as reported by Thorp, Rose, McCullough and others.
Dr James Thorp, a board-certified obstetrician with over 45 years of experience, testified to the Allison Inquiry in Canada this year. At this powerful (unofficial) parliament examination of the damage to Canadians he cited a 271-fold increase in miscarriage reporting compared to the influenza vaccine in his letter to the American Board of Obstetrics and Gynecology, a 177-fold increase in the American Association of Physicians and Surgeons journal, and a 114-fold increase in Science, Public Health Policy and the Law.
Thorp acknowledges VAERS reports do not prove causation, but he is claiming that extreme safety signals must not be ignored, and who would disagree? Further, his analyses do not stand alone. He cites Michelle Gershman in Fresno, who saw stillbirths go from one to two per quarter to multiple per week. He cites Lions Gate Hospital in Vancouver, with 13 stillbirths in 24 hours, figures supported by five care providers. He cites Czech data showing a 30% reduction in birth rates. He cites a Turkish rodent study showing 60% of primary ovarian follicles destroyed.
The Cochrane Evidence for Children
Baker promotes, and the government now funds, the flu vaccine for children down to 6 months. The Cochrane review found overall efficacy of inactivated vaccines was 64% against laboratory-confirmed influenza, but only 28% against influenza-like illness. More critically, data on hospitalisation were not available.
The Hospitalisation Fear Message
The fear message is that really sick kiddies are filling hospitals and the flu vaccine is the answer. A 2007 study calculated that with 50% vaccine efficacy (actually optimistic as flu jabs go), the number needed to vaccinate to prevent one hospitalisation ranged from 1,031 to 3,050 for children aged 6 to 23 months, and from 4,255 to 6,897 for those aged 24 to 59 months. Those numbers are nowhere in the public messaging. Parents, the chance of your child being destined to get the flu than having its infection prevented is really this small.
The Cleveland Clinic Study Showed It Doesn’t Always Work
A 2025 Cleveland Clinic study found flu vaccine recipients had a 27% higher risk of testing positive for influenza than unvaccinated employees, tracking over 53,000 employees. The same clinic published the Shrestha study on covid-19 boosters causing more covid infections. It is inconsistent to accept one while ignoring the other.
The GVDN Study
Concerning causes of vascular disease, the Global Vaccine Data Network study assessed 99 million covid-vaccinated individuals across 10 sites. Typically portrayed as reassuring, it actually confirmed safety signals for myocarditis, pericarditis, Guillain-Barré syndrome, and cerebral venous sinus thrombosis. Acute disseminated encephalomyelitis (brain inflammation) showed an observed-to-expected ratio of 3.78 after the first mRNA-1273 dose.
The GVDN is hosted by UniServices, owned by the University of Auckland. Its co-director was Dr Helen Petousis-Harris. The study was CDC-funded and terminated 13 months early after a US Department of Government Efficiency review in March 2025. It examined only 13 selected events. And these systems suffer under-reporting by factors of up to 20 to 40 times. Actual harms can be many times greater than published.
Other Safety Signals Baker Has Never Discussed
Ischaemic stroke. The CDC’s Vaccine Safety Datalink met statistical criteria to prompt investigation into ischemic stroke in people 65 and older who received the Pfizer bivalent injection.
Renal disease. A 2024 review of autoimmune kidney disease following covid jabs identified 35 cases, 74% following mRNA vaccines, with acute kidney injury the presenting feature in 43%.
These are vasculopathy-correlated conditions and deserve investigation.
The Immunology of This Winter’s Flu
The strain supposedly dominating this winter is influenza A/H3N2, subclade K. Influenza immunity is shaped by lifetime exposure. Immunology 101 says the first strain you encounter imprints your immune system most strongly. Subsequent infections and vaccinations produce progressively narrower responses. This is called original antigenic sin.
But here is the question we want to raise: does this standard model still apply to the covid-19 vaccinated?
There is evidence that repeated mRNA vaccination induces antibody class switching to IgG4 (tolerance of infections, and cancer cells, rather than attack), reduces CD4 and CD8 lymphocyte responses, and may exhaust T cell populations critical to innate immunity. If the immune system’s baseline set point has been altered, does the standard model of influenza immunity still hold?
‘Original antigenic sin’ appears to have played out for covid-19 too. This is where the first strain exposed by vaccine or infection can skew subsequent responses as the virus evolves, known as antigenic drift. A 2023 Nature paper by Cao Yunlong’s team confirmed this immune imprinting. Separately, a 2023 study in Circulation by Yonker et al detected free, unbound spike protein in adolescents who developed post-vaccine myocarditis, but not in asymptomatic controls.
If original antigenic sin has already played out for covid-19, why can we not ask whether it also affects immunity to influenza?
Finally, ‘vaccine interference’ is recognised in immunology, where one vaccine might suppress resistance to other infections. The 2019 Department of Defense study by Wolff examined virus interference and found an odds ratio of 1.36 for seasonal coronaviruses among influenza-vaccinated personnel, though the study’s overall conclusion – perhaps as insurance to get published – was that there was little to no evidence supporting virus interference
So What Has Changed?
New Zealand has had reliably predictable influenza pandemics before and coped far better. Although it had its moments the health system was not overwhelmed every winter. The hospitals did not fill with children in respiratory distress every year.
So what is different this time?
The rise in sudden deaths, cancer, excess mortality, the increase in long-term sickness, the overwhelmed paediatric wards – none of these are explained by influenza alone. Something has altered the baseline health of the population.
Baker’s answer is more vaccination. Our response is a question, though clearly rhetorical. What if the immune-skewing, clot-forming interventions of the past five years are part of the explanation, not the solution?
Conclusion
The relentless promotion of yet more vaccines for the ills of the health system is worse than fiddling while Rome burns. It is adding petrol, in the form of the gene transfer modified RNA jabs, while the absolute silence on non-drug strategies such as vitamin D, nutrients, rinses and gargles – not to mention quality sleep, stress reduction, exercise – is akin to turning off the fire hose.
But, generally, vaccine hesitancy is increasing, so Professor Baker scrabbling around for something good to say about one of them is a predictable response. They will be telling us soon that mRNA jabs cure cancer, not cause it. But wait..
What is your assessment? Is Baker’s cardiovascular claim a distraction from the real safety questions? Are covid-vaccinated children and adults at particular risk from all infections including influenza? And why do modifiable risk factors like vitamin D, zinc, and NAC receive so little public health attention when the evidence for them is far stronger than the evidence for some vaccines?
We are pleased to feature this important contribution from a founding member of New Zealand Doctors Speaking Out with Science (NZDSOS).
Who Knew? What Did They Know? And When Did They Know It?
I was in the USA when the “novel Coronavirus” was announced to the world in February 2020. All legacy media outlets in the USA incessantly used the word “novel”. I was exhausted with this word after a few days and decided I would find out what was so novel about it.
Immediately, upon a cursory search of the PubMed data base, I found a paper published by Dr J Claude Perez in February 2020 describing the “synthetic origins of the novel coronavirus” (see reference 1). It detailed what seemed to be a gene-spliced bioweapon with fragments of prior infectious agents known as HIV, influenza A, and SARS-1. It was clear that that the intention behind this “novel” construct was to make a highly transmissible illness combining the flu and SARS-1, and preferably also make it capable of causing chronic immune suppression and recurring illness. It seemed the bioweapon industry wanted for it to be “the gift that keeps on giving” (to them). So far, the hopes of its developers seem to be fulfilled and no major penalties have been incurred.
If “little ol’ me” could find this article, I am certain that the eminent Dr Fauxci (dis-spelled deliberately) and his NZ proxy, Dr Bloomfield were able to find this article in the public domain. Yet the mass hysteria of the Chinese wet market theory ensued. This allowed the officials to have plausible deniability of the synthetic bioweapon and created a “natural” explanation of how the bioweapon might have acquired its ability to target the human vascular ACE-2 receptor (the pangolin apparently has an ACE-2 receptor that most resembles those in humans – publications in 2020, references 2,3). Most of us never heard of a pangolin until the last frame of The Jungle Book (was this Hollywood foreshadowing in 2016? NZDSOS has written about media being used for predictive programming here).
He Knew! Evidence of a Pre-plandemic
Dr Anthony Fauxci had announced, with certainty, at a NIAID meeting in 2017 that “Donald Trump would be faced with a serious pandemic during his presidency”. Thus it was cold and calculated. In December 2016 (after Trump’s election the month before) congress had quietly agreed, to lift the moratorium on “Gain of Function research” that had been put in place during the Obama administration in 2012. This technology was originally developed at the University of North Carolina at Chapel Hill. It was exported to Wuhan in 2012 and subsequently funded through the Eco Health Alliance, with US taxpayer dollars, and with Dr Fauxci’s full knowledge and support. All of this information is in the public domain and beyond dispute.
Dr David Martin has catalogued the intellectual patents involved with all of this, and the many other public health false flags, since especially around 2012, but actually following the money trail back to 1999. Voices raising these issues continue to be censured. There remains no accountability for the wrongs that have been suffered around the world.
The Active Deployment Scenario
Personally, I do not actually think it was a “lab leak” that killed so many people. I say this because Washington State was among the first states to close down after a single case of covid-19 was diagnosed in an individual in an aged care facility who had not travelled to China or had any visitors who did so. Perhaps this was a nod to the Gates Foundation, which had given the University of Washington about $1.5 billion in aggregate for several years prior to the plandemic? Washington state was to then serve as the example for other states to follow. In my reasonable belief, there was active deployment of the bioweapon to major cities around the world from late October 2019 up until the global pandemic was announced. Early in the pandemic response, Dr’s Fauxci and Birx were seen wearing white lab coats bearing the seal of the Institute for Health Metrics and Evaluation at the University of Washington. The University of Washington and Johns Hopkins (hugely funded by the Rockefeller Foundation, and the epicenter of the infamous Flexner report which ushered in petrochemical medicine) became America’s “podium of public health truth”.
Cranking Up the Fear
I watched the USA propaganda machine (85% funded by Big Pharma, especially Pfizer) churn fear every day to create terror in the world’s population and drive demand for relief. The madness of virtue signaling by wearing a mask in your car alone became commonplace. I walked the dog every day without a mask. Terrified people would leave their yards when they saw me and seek shelter in their homes even though I was over 40 feet away. President Trump closed USA borders to China but really wanted to keep USA shops open to save small businesses. Drs Fauxci and Birx knew better…. Like New Zealand, small businesses in America were obliterated by their pandemic response and our respective western economies have still not recovered to this day.
The Suppression of Treatments and the Vaccine Push
From April 2020-August 2020 New Zealand was in lockdown and I could not return to what had become my home since 2010. It was clear to me that the globalist public health agenda was to suppress available potential treatments for the pandemic and have people die waiting for the communion wafer vaccine in order to pressure Big Pharma funding from Congress.
So-called cases were created by overly sensitive PCR tests that were picking up random gene fragments including of influenza (which all but disappeared from 2020-2021). Never mind that it was settled public health science to avoid vaccination in the midst of a pandemic as this results in the clonal expansion of new variants that are not prevented by the vaccine (Omicron and Delta developed when the vaccine targeted the Alpha strain, etc). The globalist corporations needed more public desperation to force Trump’s hand and get the American public’s intellectual buy-in to a vaccine being the “only scientific approach”. The grand scheme compelled the US Congress to approve a trillion dollars for the pandemic response. The NZ parliament put forth an estimated over $60 billion NZD of taxpayer’s hard-earned money for the NZ pandemic response. India purchased $5.00/person covid packs with Zinc, ivermectin and 2 weeks of doxycycline to manage secondary bacterial infection, whilst New Zealand spent about $14,000 per person on an untested gene product that was dangerous and did not reduce transmission.
Hydroxychloroquine: The Buried Solution
Hydroxychloroquine (HCQ) had been shown to be effective against SARS-1 for almost 20 years. Early in 2020, President Trump had suggested HCQ as a plausible treatment of SARS-2 (covid-19). But the concurrent disease known as Trump Derangement Syndrome prevailed. Trump’s suggestion obviously horrified Dr Fauxci and his Big Pharma handlers who had aspirations of Emergency Use Authorisations (EUAs) and the deployment of mRNA technology without FDA oversight. Trump faced profound ridicule and humiliation from his own public health officials for advocating the use of HCQ for the critically ill. It was all but buried as an option, simply due to politics.
Any USA physician who prescribed HCQ for covid-19 faced severe scrutiny and censure from their medical boards. Pharmacies were told to sequester the supply to prevent it from being disseminated for people in need, as it did not fit the narrative “that there was no effective treatment” as they pushed for EUA for mRNA technology that was never appropriately tested. Scientific fraud ran rampant as medical journals jockeyed for Big Pharma funding and, in retrospect, it is very clear which journals were working for and against the public interest during this time. Will they ever be held accountable?
My Communications with the NZ Government in August 2020
In August 2020 the first lockdown had ended, the New Zealand border had opened, but quarantine was required. I finished 60 hours of Continuing Medical Education whilst in quarantine. I was very worried about being able to travel freely in the future, so I wrote to the key members of the NZ government to discern what might be their future plans. I advocated for “Plan B” that Dr Simon Thornley had put forth (no further lockdowns, no mandates, not isolating the healthy, etc). I sent them the articles listed in references 3-6 citing the safety and efficacy of treatment with hydroxychloroquine and azithromycin in addition to dexamethasone for people with serious illness from covid-19.
Public health officials had made much ado about cardiac risks from HCQ, but this had been previously debunked by a 2016 study which they all ignored (reference 6). Innumerable studies showing therapeutic efficacy for Ivermectin then followed, along with prevention by healthy vitamin D levels (7). This was all available prior to our NZ vaccine roll out and big public spend. Despite these multiple treatment options available in 2020, New Zealand public health officials were only allowed to consider treatment with the untested experimental inoculation for covid-19. Why???
They all knew, in August 2020, that there was effective treatment for covid-19 and thus no indication for an EUA which allowed them to proceed with the investigational mRNA inoculation without proper scrutiny and regulatory oversight. The information that I provided on dexamethasone and HCQ was ignored, the EUA granted, and we then squandered countless lives and treasure in 2021-2023, on an ineffective mRNA inoculation that failed to reduce transmission and caused myocarditis and blood clots resulting in thousands of deaths (as documented in Pfizer’s own documents that they attempted to “classify” for 75 years).
The NZ Government’s Role and Accountability
The then Health Minister, Chris Hipkins, has since tried publicly to side-step any responsibility of the Labour government for the covid vaccine debacle and their imposed restrictions on social gathering, travel restrictions, working unless jabbed, creating a “two- tiered” society, social distancing, mask lunacy, hypnotic traffic light nonsense, etc. He just gave it all a shrug and said, “it was never a government mandate”. It technically wasn’t because it was actually “WorkSafe” that was the enforcer and held the power to shut down businesses unless their employees were in compliance with the government recommendations. So…we only really had to do it if we wanted to keep our jobs so that we could feed our families and pay our bills? This, by any other name, is called “economic extortion” and the Labour government was totally on board with it. We should never forget this.
Neither should we forget the fracture of friendships and families caused by these ridiculous authoritarian policies. We learned how quickly we could become a nation of sanctimonious snitches who gave up our freedom and played into the global plans to create cashless societies and usher in their digital controls. The programming of society to think of cash as contagion (instead of freedom and privacy) was introduced. Would we do it all again? We will likely have another test of our mettle in the near future.
Bloomfield Trashes Medical Safety of Pregnant Women
Sir Dr Ashley Bloomfield was always in lock step with advice from USA doctors Fauxci and Birx. He knew, or should have known, about the risks to pregnant women. Dr Fauxci knew this risk, as has been shown in his text messages released just recently. The public were deliberately defrauded regarding these injections being “safe and effective” for pregnant women. The New England Journal of Medicine provided “cover” for them and simultaneously introduced the woke concept of “pregnant persons” although there were no pregnant men in the study (8). Its former editor-in-chief, Dr Marcia Angell, was a longstanding critic of pharmaceutical-industry influence on medical research and journals, and later wrote extensively about concerns surrounding industry-sponsored clinical research (9).
With the understanding that spike proteins attacked the ACE2 receptor of blood vessels, it was totally logical that this mRNA inoculation would cause miscarriages, since a developing baby must have a healthy blood supply. I recall that our highly esteemed and decorated, Sir Dr Bloomfield pounded away, day after day, recommending an unproven and poorly tested mRNA inoculation to pregnant women in New Zealand and eventually to teens and to children. In their vulnerable state, pregnant women were afraid not to have the injection. I am personally aware of midwives who were censured and lost everything for standing against this.
Any midwife paying attention would have noted a substantial drop off in live births after the covid-19 mRNA inoculation was rolled out to pregnant women. Many couples are now facing the inability to conceive as a result of the mRNA inoculation. Will Sir Dr Bloomfield retain his order of merit?
Betrayal of the Nation Used to be a Capital Offence
To me, every politician in office from 2019 to 2023 has betrayed our nation. Some were paid handsomely for their participation in big pharmaceutical contracts in exchange for our lives and treasure, to the gain of foreign corporations. In my view, Big Pharma absolutely abused New Zealand, as severely as it did the USA, and gave a few politicians lots of money, to enroll our citizens in a large-scale un-consented biological experiment. The profound regional death disparities, brought to light by whistleblower Barry Young’s Health NZ data, confirm that there were many different batch toxicities (aka sub-experiments), some more lethal than others. Peer-reviewed papers presented to officials by NZDSOS are strong corroborating evidence.
In my view, not one politician in a major party stood against the government covid response when it really mattered. The Labour government literally destroyed small businesses throughout New Zealand and thereby gutted our economy. These chickens have come home to roost under Chris Luxon, but they were hatched under Chris Hipkins and the Labour party. David Seymour was even more strident than Jacinda Ardern in advocating for restrictive public health policies in 2021 and cannot be trusted despite now making noises about government fiscal restraint.
Fear For our Future
When Kiwis are in pain, they are prone to congregate under the perceived soft underbelly of a Labour government. Our memories of how we got to our present economic downturn seem to have faded much too quickly. I do not like the division sown by our current government and the dismantling of our cultural heritage. The biggest fear of our government is that the people of NZ will rise above the government race-baiting and become one voice for our free land. The Tiriti O Waitangi, and its secondary legislation, remains the best defense against an outright takeover of our land and resources by multi-national corporate interests. The wolf, in the sheep’s clothing of co-governance, is at the door.
This is precisely why and how our Parliament is trying to weaponise Te Tiriti against us to bring more in the way of race-based fragmentation. I do not like the wholesale laying down of our sovereignty to technocrats and multinational corporations that is the end-game of successive governments (Gene Technology Bill, AI data centres etc) whose only functional arm seems to be the Ministry of Business, Innovation and Employment (through which foreign investment is funneled). On election day, I will pray, hold my nose, and try to select the least of the evils before me. The instinct to scorn the lot of them runs strong, but there are some new freedom-minded candidates in the mix, bless their yet to be bloodied socks.
A Call to Bring to Account
I will continue to hope that those who deliberately “pulled the wool over our eyes”, and cost too many lives and generations of wealth, will be held accountable. We must not be too quick to forget history, lest we repeat it. We cannot afford the sequel that awaits us if we are unwise or if we tolerate less than “free and fair” elections. Key people in Government (Ardern, Hipkins, and Bloomfield, to name but a few) knew in August 2020 (if not before) that there was probably no need for the EUA for the covid mRNA inoculation and yet they did it anyway. They would have known people were being hurt later but carried on anyway then too.
Be strategic with your vote (whilst knowing you are playing in a system which is hurting us badly). Stand with those who stood for you or who will do so now – and let’s welcome back those who are only just recovering their senses. May God Defend New Zealand from all of her enemies within and without.
References:
1. Jean- Claude Perez. Wuhan Covid-19 Synthetic Origins and Evolution. Int Journal of Research 8(2) 285-324. Feb 2020.
2. Zhang, T, et al. Probable Pangolin Origin of SARS-CoV 2 Associated with the Covid-19 Outbreak. Current Biology, Vol 30 issue 7, April 06, 2020.
3. Wang, NS, et al. Molecular basis of cross-species ACE2 interactions with SARS-CoV2-like viruses of pangolin origin. . 2021. EPA (Hero ID 7696973).
4. Arshad, S, et al. Treatment with Hydroxychloroquine, Azithromycin and combination in patients hospitalized with Covid 19. International J Infectious Disease; June 2020
5. Horby, et al. Dexamethasone in Hospitalized patients with Covid-19-Preliminary Report, NEJM 2020
6. Sharma, TS Hydroxychloroquine use is associated with decreased cardiovascular risk in Rheumatoid arthritis patients. J American Heart Association 2016.
7. L Borsche, et al. Covid-19 Mortality risk correlates inversely with Vitamin D3 status, and a Mortality rate close to zero could theoretically be achieved at 50 ng/ml 25(OH) D3: Results of a Systemic Review and Meta Analysis. Nurients. 2021 October 14;13 (10).
8. Shimabukuro TT, et al. Preliminary findings of mRNA Covid-19 Vaccine safety in pregnant persons. N Engl J Med. 2021;384:2273-2282.
9. Angell, M. Industry-Sponsored Clinical Research: A Broken System. JAMA. 2008;300(9):1069-1071.
Below we have examined yet more cases of fatal myocarditis in New Zealand since 2021. In most of these cases the coroner does not appear to have asked the obvious questions.
In making the point yet again that these cases are poorly assessed, we note that far more people get pericarditis and myocarditis than go on to die suddenly from it. Are all these people similarly diverted from understanding a likely cause? Certainly not the many hundreds whose vaccine causation is accepted by ACC. But what about those who never know to make a claim, or who are turned down as they haven’t waited up to 2 years for a cardiac MRI?
Watch: Ashley Bloomfield Announcing Myocarditis 21 July 2021
We are aware that sudden death from myocarditis happened prior to covid, often ‘presumed viral’ but with no virus documented.
However, a provisionally-consented (due to absent safety information) genetic intervention, acknowledged to be a cause of myocarditis, was introduced into the population in 2021.
(Un)common sense suggests it should be on the list of things to consider when determining what caused someone’s death. And we know there is a long queue for coronial investigations of deaths which are now years ago. And these delays have been the reason given too for refusing to release up to date cancer death figures we have been chasing.
In some of the cases below the person is said to have died from myocarditis caused by covid infection, but if they have previously been vaccinated how is it ascertained whether it was vaccination, infection or both? We know how this could be done, but such testing is not accessed in NZ.
The information below comes from NZ coroner (lawyer) reports. We have not seen post-mortem (doctor) reports for these people and it is possible there is further relevant information contained in them. However, for deaths reported to the coroner, the coroner’s report is the official public record noting a person’s cause of death.
Case 1:
A 42 yr old woman, working in the mandated education field was found dead at home after she failed to respond to phone calls in early 2022. In this case the pathologist and coroner have commented on covid vaccinations noting she had had three covid vaccinations.
The coroner documented that the cause of death was acute lymphocytic myocarditis and that it “may be idiopathic, or due to viral, fungal or bacterial infection, or autoimmune or hypersensitivity disorders”.
The pathologist noted that, “given the time since administration of COVID vaccination doses (13 July 2021, 3 August 2021, and 23 January 2022), and given it is a lymphocytic myocarditis (not the eosinophilic myocarditis seen in vaccine-related myocarditis), the development of myocarditis in this case is not related to vaccination”.
Really?? How did she determine that? What did cause the myocarditis then? Sudden death following silent myocarditis CAN happen months or even years later. And various immune cells can predominate in inflamed tissues. In medical speak, idiopathic means “just one of those things”. But there is ALWAYS an explanation for sudden death, if you look hard enough and consider all information.
By the time she died, all four of the New Zealanders who have officially been recognised as being killed by the covid vaccination were dead. Only one of these deaths was from eosinophilic myocarditis (eosinophils and lymphocytes are different types of white blood cells found in inflammation), and that was the first recognised death – a 57 yr old lady whose case was written up in a medical journal.
Rory Nairn died from myocarditis, the 13 yr old Wellington boy from acute lymphocytic myocarditis and Amanda Smees from myocarditis in the post vaccination period.
Was her death reported to CARM?
Did the Independent Safety Monitoring Board (ISMB) review her case and undertake a formal causality assessment? What was the outcome?
Or was the pathologist’s declaration sufficient? If so, is the pathologist trained in pharmacovigilance?
Where does the responsibility lie – with the pathologist, the coroner, CARM, ISMB, GP, ACC, someone else?
Should the mandating institution bear any responsibility if her death was due to covid vaccination?
Curiously Coroner R Kay was the coroner responsible for determining cause of death for the teen who we say died of post-vaccine acute lymphocytic myocarditis. The coroner said he couldn’t rule it out. The pathologist’s opinion is odd in this case – that lymphocytic myocarditis does not occur post covid vaccination!
So many questions, incorrect evidence, and no-one to answer.
Case 2:
A previously healthy 33 yr old Fijian-Indian healthcare worker (presumably subject to covid vaccine mandates) collapsed suddenly at a party in early 2022. She was resuscitated sufficiently to get to hospital. However, she died 5 days later and post mortem examination showed myocarditis as well as a small focus of inflammation in the brain (encephalitis).
The coroner, despite noting that myocarditis “is usually viral in origin, but it can also be due to drugs, other infections, autoimmune diseases etc.”, has not recorded consideration of a particular drug known to cause myocarditis (i.e. covid vaccination).
The pathologist concluded that this person had “a subclinical viral infection” but the coroner has not documented evidence of any particular virus. Her family was referred to the Cardiac Inherited Diseases Group (CIDG) for assessment but no outcome from that assessment is included in the coroner report.
Cause of death: • Hypoxic/ischaemic encephalopathy (brain damage due to lack of oxygen) • Myocarditis (presumed viral)
This lady had inflammation in two critical organs. The late German pathologist Dr Arne Burkhardt provided second opinion post mortem findings for family members who were concerned that covid vaccination was involved in a loved one’s death. He discussed some of his findings prior to his death in 2023. Of relevance to this case, he described finding inflammation and vasculitis in most of the brain samples he examined but said often it was subtle and could easily be missed if not specifically looked for.
Did anyone ask the appropriate questions?
Watch: Dr Arne Burkhardt Discussing Brain Inflammation
In mid 2022 a 45 yr old went surfing but told a friend he was not feeling well as he came out of the ocean. He went to his vehicle and collapsed. Prompt resucitation failed. He had had ‘cold’ symptoms the week prior but had not tested for covid.
He worked in a mandated school setting. The coroner noted he had received his last covid vaccination in 2021.
On post mortem examination, the pathologist found both lymphocytic myocarditis and lymphocytic aortitis (inflammation of the aorta which is the large artery in the chest and abdomen). The pathologist noted that this combination was well-described in the case of covid-19 infection. He did not mention that they are also both well recognised adverse effects of covid vaccination.
A post-mortem PCR test for covid-19 was negative.
Toxicology was negative for relevant drugs.
The coroner accepted the pathologist’s explanation that a negative covid PCR test did not exclude covid-19 infection contributing to the death “because the myocarditis identified was a late event which could occur days to weeks after the onset of infection and is an autoimmune phenomenon”.
Official cause of death: • Lymphocytic myocarditis • Recent COVID-19 infection
More relevant and likely, myocarditis and aortitis are both autoimmune and/or inflammatory phenomena that follow covid vaccination!
How long can the Pfizer mRNA persist in an individual person? How long can the spike protein get produced for? How long can the spike protein persist? Peer-reviewed research has answered: up to YEARS.
Are the risks of infection following previous vaccination cumulative i.e. following two vaccines, does a covid infection equal a third dose of spike protein?
It is our view that covid vaccination is much more likely to be the cause of death than an unproven covid infection. This is another case where more than one organ has been affected.
It remains essential to ask: was this death referred to CARM and the ISMB? Did a pharmacovigilance expert do a causality assessment?
Should an ACC claim be made for vaccine failure? We were all advised that covid vaccination would stop us getting sick and stop us dying! It was approved to PREVENT covid-19. This man may have had his life prevented yet his cause of death is supposedly due adverse effects from covid infection.
Watch: Ardern Announcing, “You Won’t Get Sick and You Won’t Die”
Case 4:
A 22 yr old young man collapsed in early 2023 while out deer-stalking with friends. He was unable to be resuscitated.
His cause of death is recorded as sudden cardiac death with features of cardiomyopathy and myocarditis.
In the brief report there is no documentation of covid vaccination or infection status or cause of myocarditis.
Had he received covid vaccines, which dates, which batch number(s)?
Was his death reported to CARM? Has anyone done a causality assessment?
Did anyone ask the relevant questions?
Case 5:
A 21 yr old young woman died suddenly at work in late 2023. She had recently seen her GP for migraine headaches, dermatitis, anxiety, tremors, sweaty hands, and a random racing heart. Post mortem showed changes in the lungs and heart consistent with a recent viral infection that had involved the heart. However, no virus was identified in the coroner report. Myocarditis was widespread, which could cause death through the generation of a cardiac arrhythmia.
There was no underlying genetic condition on testing.
Cause of death: lymphocytic myocarditis.
We don’t know if she had received covid vaccination(s) but the list of complaints she had seen her GP with certainly sounds similar to what many other vaccine-injured Kiwis are experiencing.
Did anyone ask whether she had received covid vaccinations. If so, how many, when, what batch numbers?
Has anyone done a causality assessment?
Case 6:
A 44 yr old caregiver (so possibly mandated) died in her sleep in early 2025. Her health had been deteriorating for a few months prior, and she was awaiting an urgent neurological appointment. She had lost all the strength in her legs on the day before her death.
A post mortem examination determined that she experienced sudden cardiac death due to myocarditis (lymphocytic). However, features of motor neuron disease were also present which would explain her worsening neurological symptoms.
This is another unusual case – with two separate serious diagnoses in a relatively young woman. Covid vaccination could provide a single causative factor with its delivery to the heart and nervous system and propensity for causing autoimmune disease. No mention of this possibility in the coroner’s report.
Once again did anyone consider what might have caused these two conditions and exclude the obvious?
Do You See a Pattern Here?
As previously noted, we are more than disappointed and concerned by officials apparently looking the other way. In fact we are outraged at the shonkily explained loss of life and the derelict job these poor families are getting.
We have been unable to get answers. It is up to each and every New Zealander who can smell a rat to ask questions at every opportunity and demand change in the system.
This site is for informational purposes only and does not offer professional medical advice, diagnosis, or treatment—users should consult their healthcare professionals for any medical concerns.